EHR software development for a multi-clinic physical therapy group
Specialty groups often run on EHRs built for another kind of practice. This is how we'd build a custom EHR for a multi-clinic physical therapy group, around episodes of care, plans of care and the billing rules therapists live with every day.
Industry
Outpatient physical therapy
Typical timeline
24–28 weeks
Typical team
7 people

The situation
Picture an outpatient physical therapy group with 38 clinics across Georgia and the Carolinas, about 220 therapists and assistants, and roughly 9,000 visits a week. It runs on a general-purpose EHR that was built for physician practices and adapted for therapy.
The fit is poor. Therapists spend 15 to 20 minutes after each visit on documentation because the templates don't follow how therapy notes are written. Plans of care and re-certification dates are tracked in a spreadsheet, so some visits happen after a plan has lapsed and can't be billed. Timed CPT codes are counted by hand, which leads to under-billing and denials. Outcome scores such as the Oswestry or LEFS are collected on paper and never reach a report.
The group has looked at specialist PT systems, but its own clinical protocols, a direct-employer program and the way it runs scheduling across clinics don't fit any of them well. It is considering EHR software development: a system built around therapy, owned by the group.
Signs this blueprint fits you
- Your clinicians document in an EHR built for a different specialty.
- Plans of care, authorizations or visit limits are tracked outside the EHR.
- Coding and billing rules specific to your specialty are applied by hand.
- You collect outcome measures but can't report on them.
- You have the scale to justify owning your platform, and the patience for a phased build.
What we'd build
- Therapy documentation: initial evaluations, daily notes, progress reports and discharge summaries built around therapy templates, with previous findings carried forward and quick-pick exercises.
- Plan of care management with goals, frequency, duration, physician signatures and re-certification due dates that block scheduling when a plan has lapsed.
- Timed-code billing support that totals treatment minutes per code, applies the units rule your payers follow, and flags notes that don't support the units billed.
- Outcome measures collected on a tablet or by text link, scored automatically and charted over the episode of care.
- Multi-clinic scheduling with therapist availability, visit limits per authorization and waitlists.
- A patient app for home exercise programs, appointment reminders and outcome questionnaires.
- Integrations with a clearinghouse for claims and eligibility, a practice management or billing service, and FHIR APIs for sharing records with referring physicians.
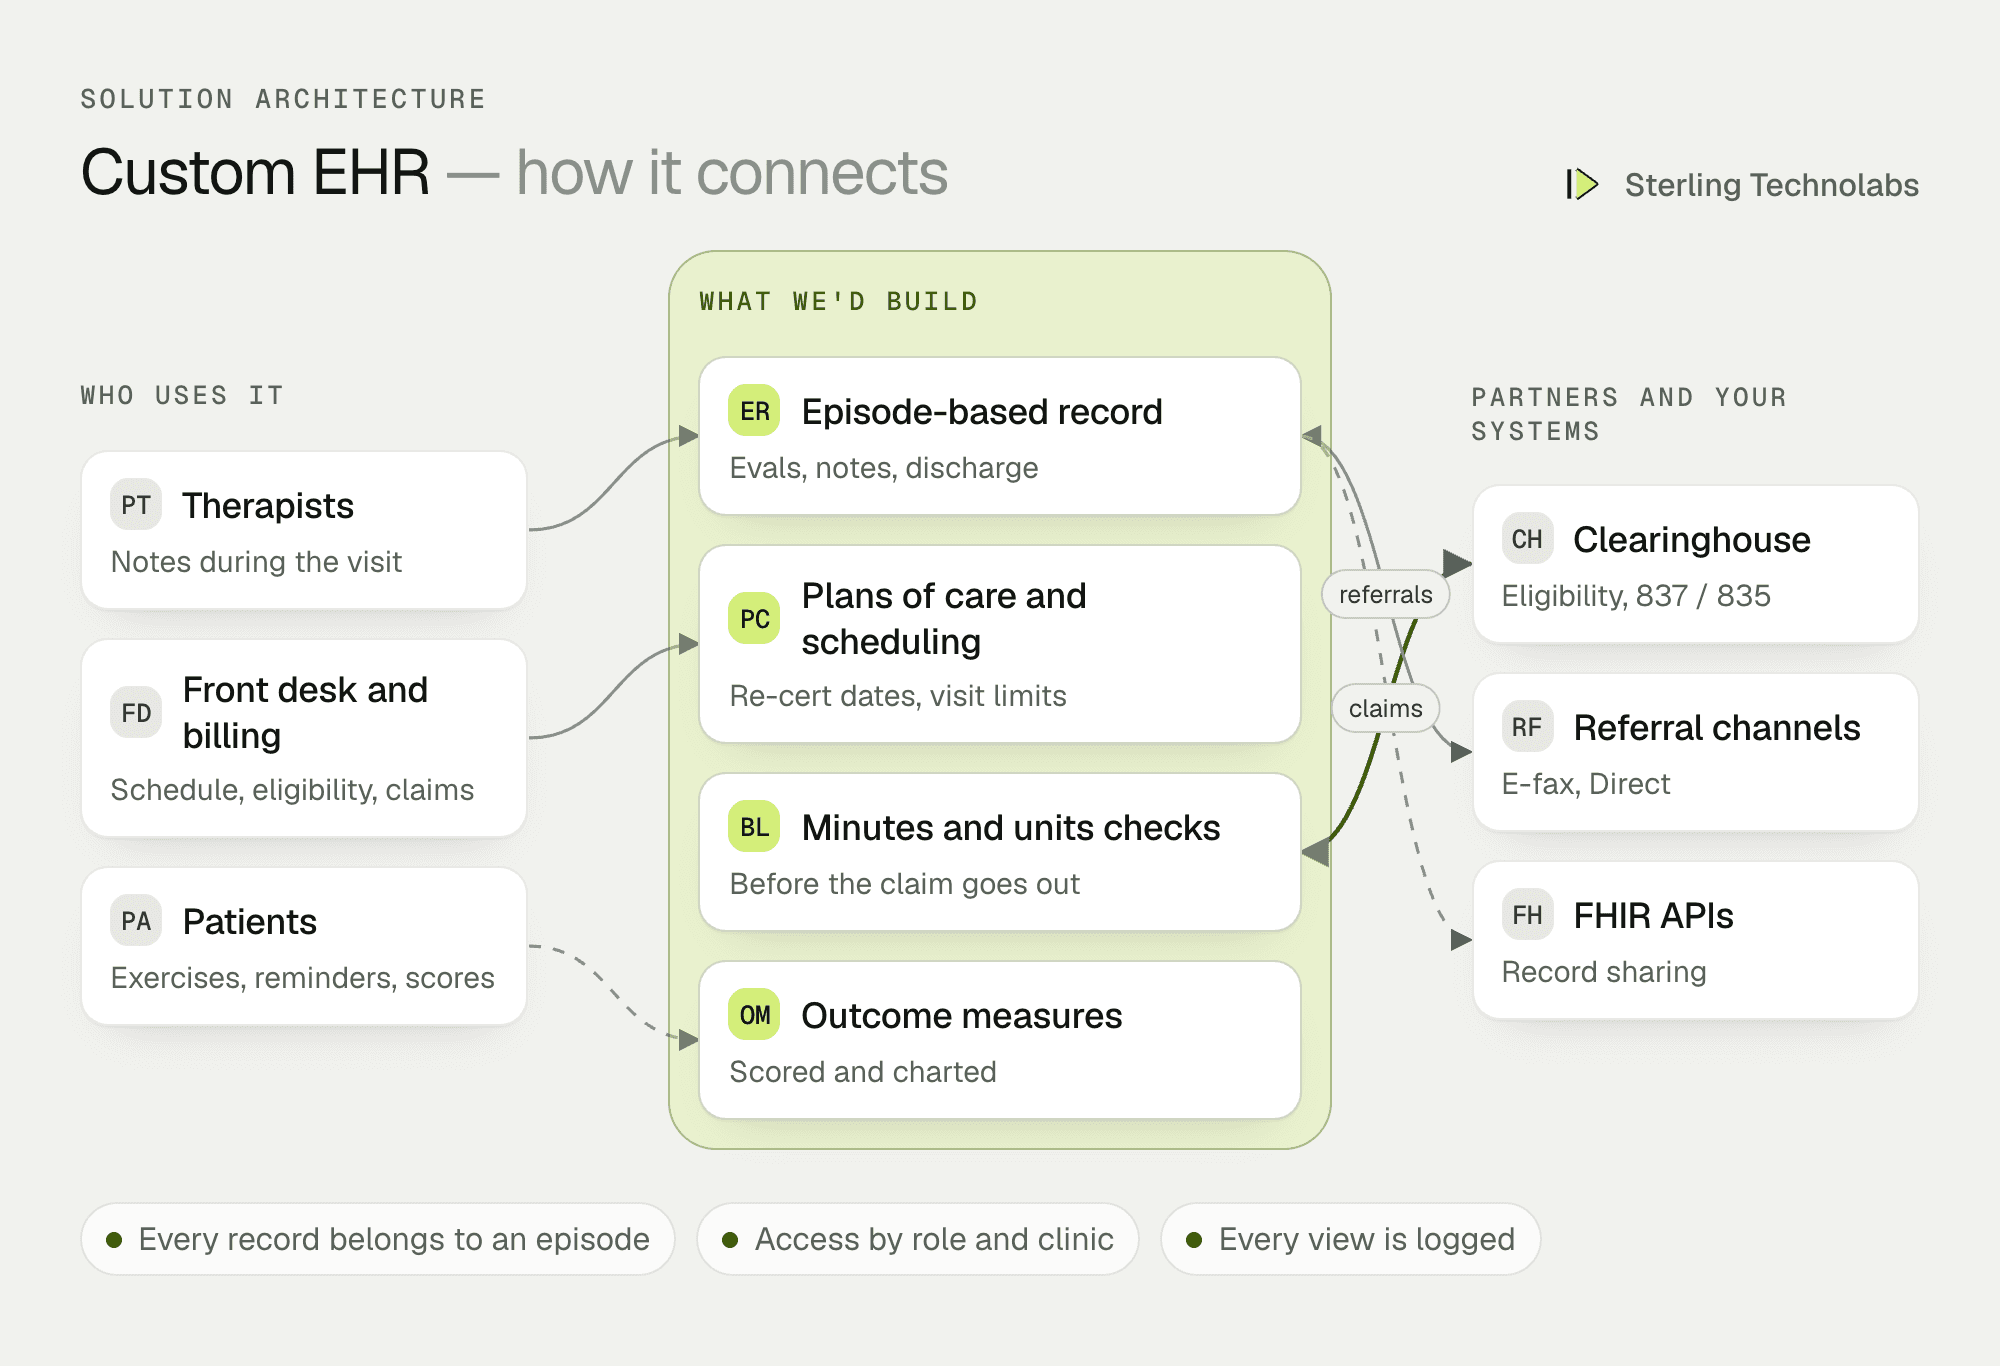
How the pieces fit
A clinical record built around episodes of care
Therapy happens in episodes: a referral, an evaluation, a plan of care, a series of visits and a discharge. The data model follows that structure, so every note, minute, outcome score and claim belongs to an episode. That is what makes plan-of-care checks, visit limits and outcome reporting possible without spreadsheets.
Billing rules in the software, not in people's heads
Each note records treatment minutes per CPT code. The system totals timed and untimed codes, calculates billable units by the rule each payer uses, and compares them with what the therapist selected. Notes that don't support the units are flagged before the claim goes out, not after a denial.
Interoperability
Referrals arrive by e-fax, portal or direct message, and are attached to a new episode. Discharge summaries go back to the referring physician. Records are exposed through FHIR APIs so other systems, patient apps and payers can request them, and so the group can meet information-sharing rules.
Security and compliance
The platform runs in a HIPAA-eligible cloud account under a business associate agreement. Access is by role and clinic, every view and change of a record is logged, data is encrypted in transit and at rest, and backups are tested. If the group needs ONC certification for a quality program, that is planned as its own phase, because certification adds testing and documentation requirements.
One visit, end to end
Here is a follow-up visit for a patient with low back pain, from check-in to a clean claim.
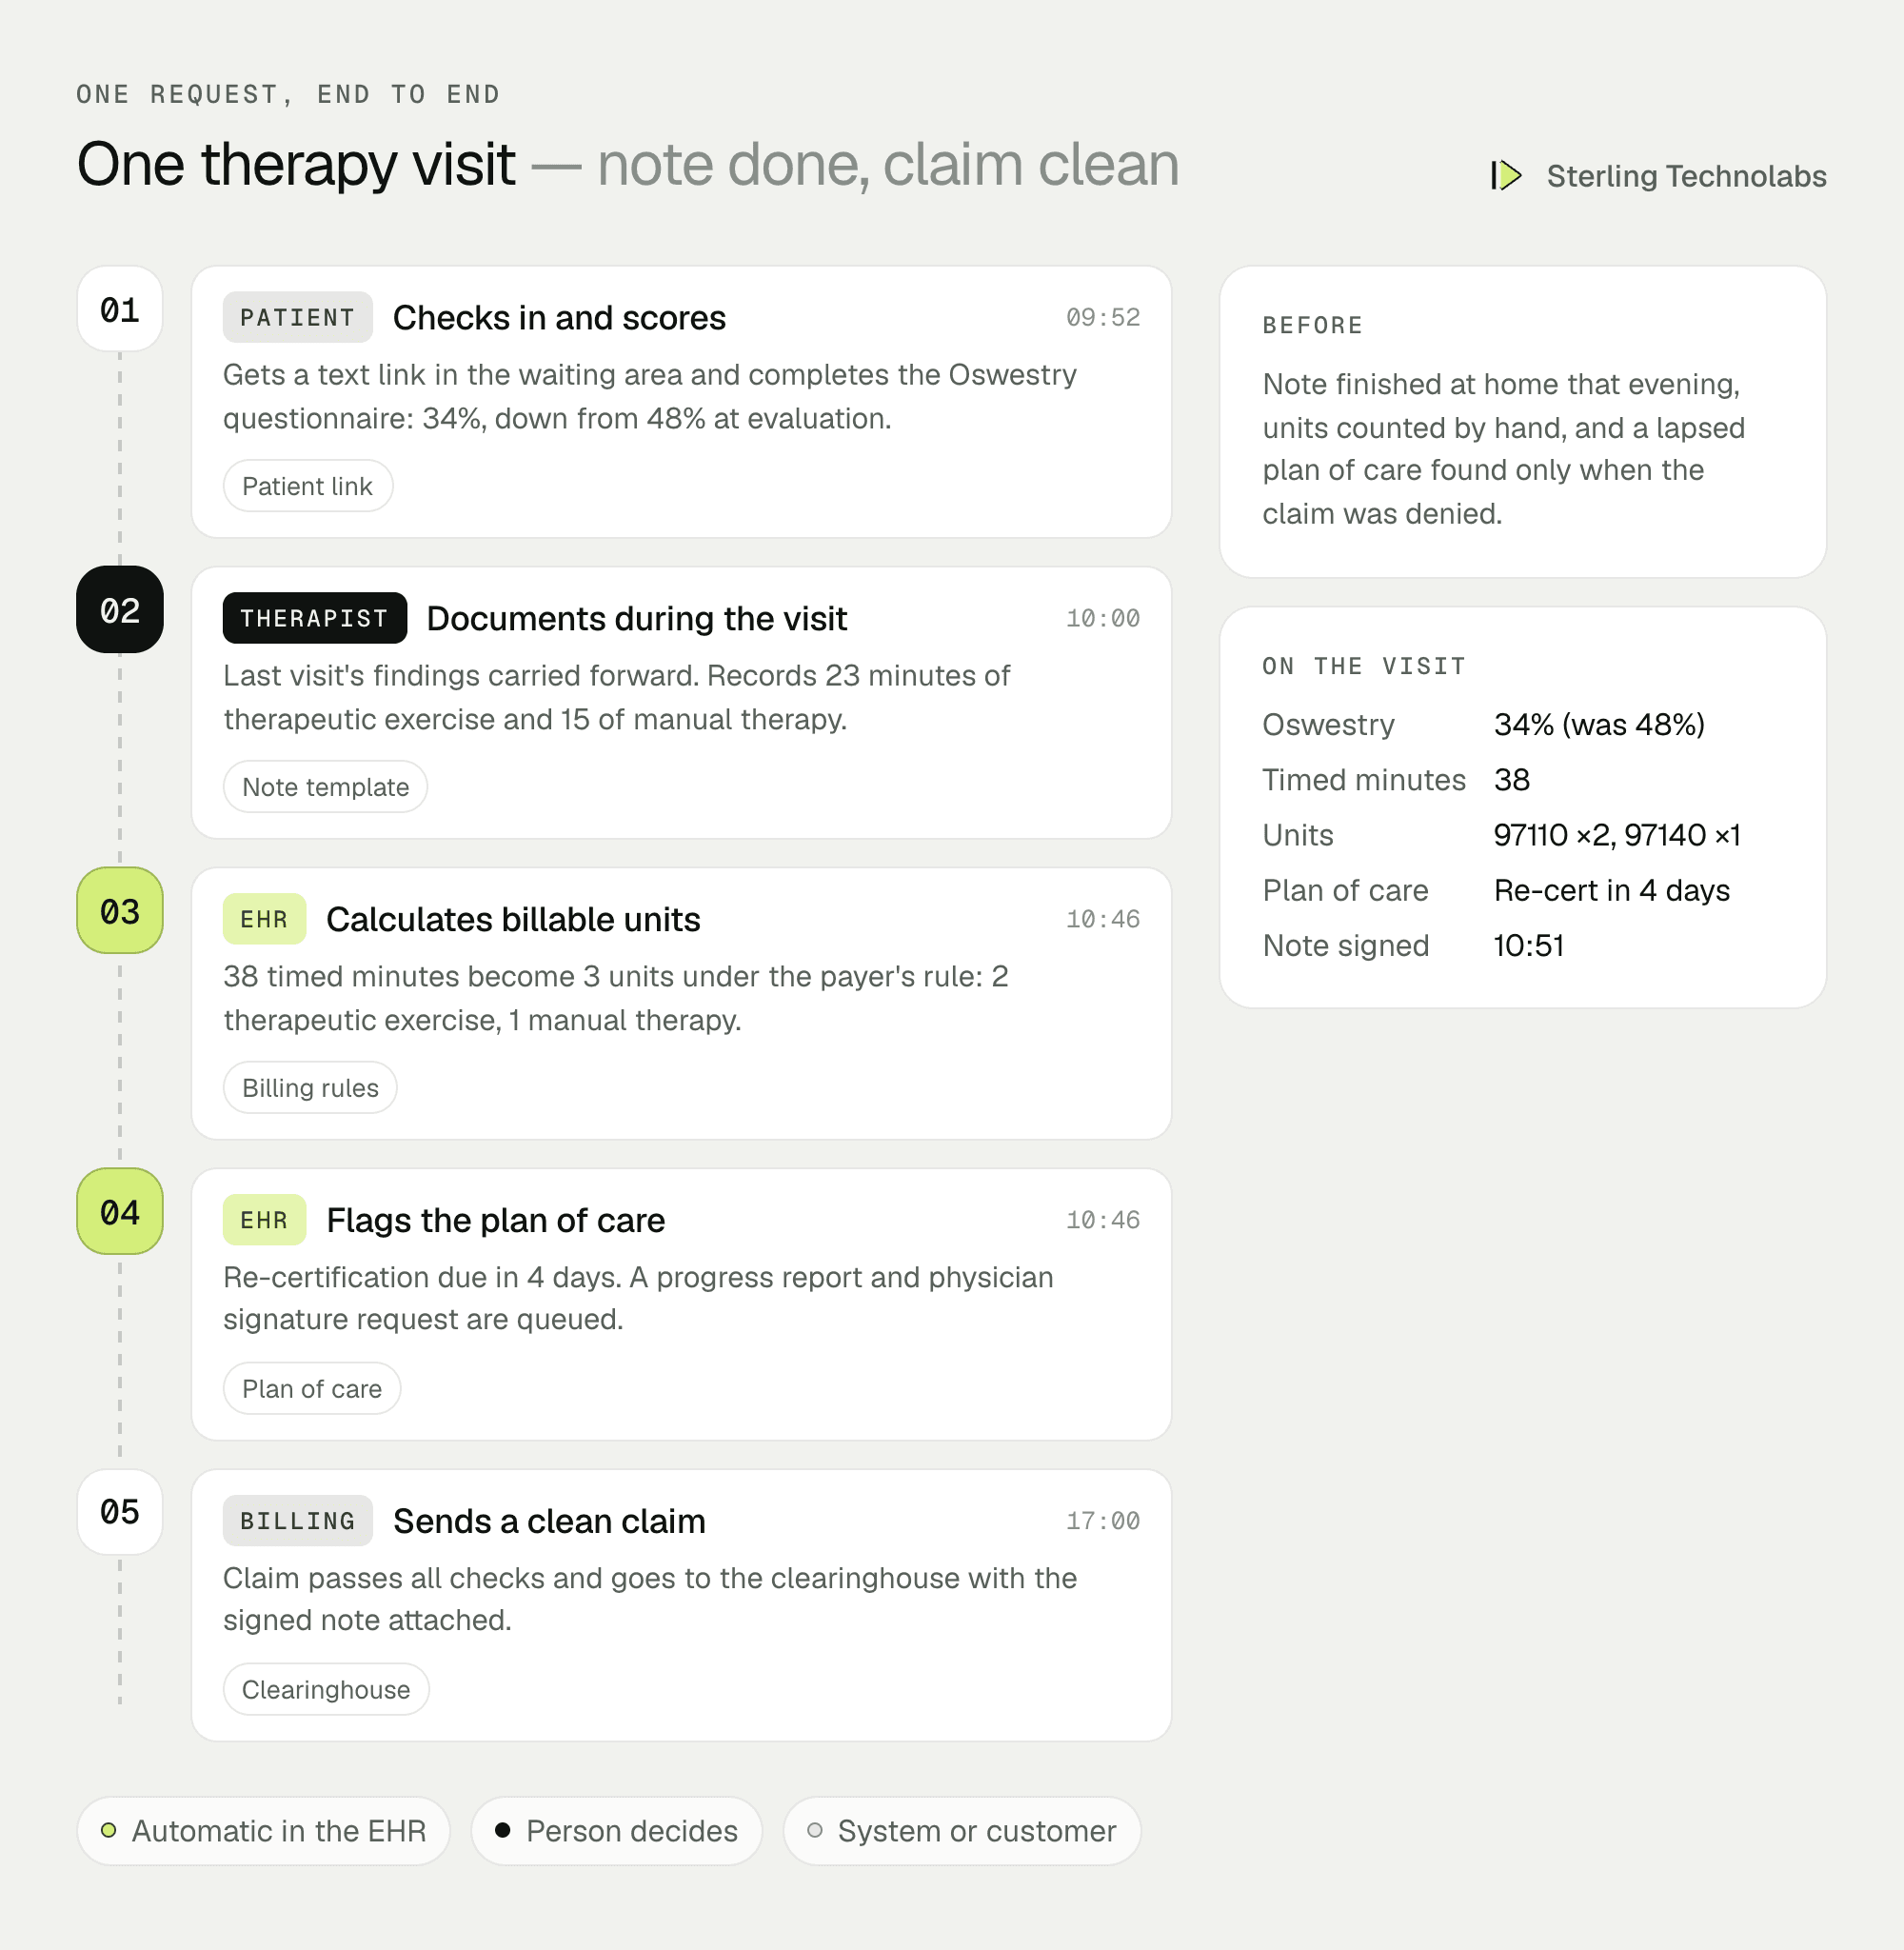
The therapist wrote the note during the visit, the units were calculated for them, and the system caught that the plan of care needed re-certification before it caused a denial.
What therapists would see
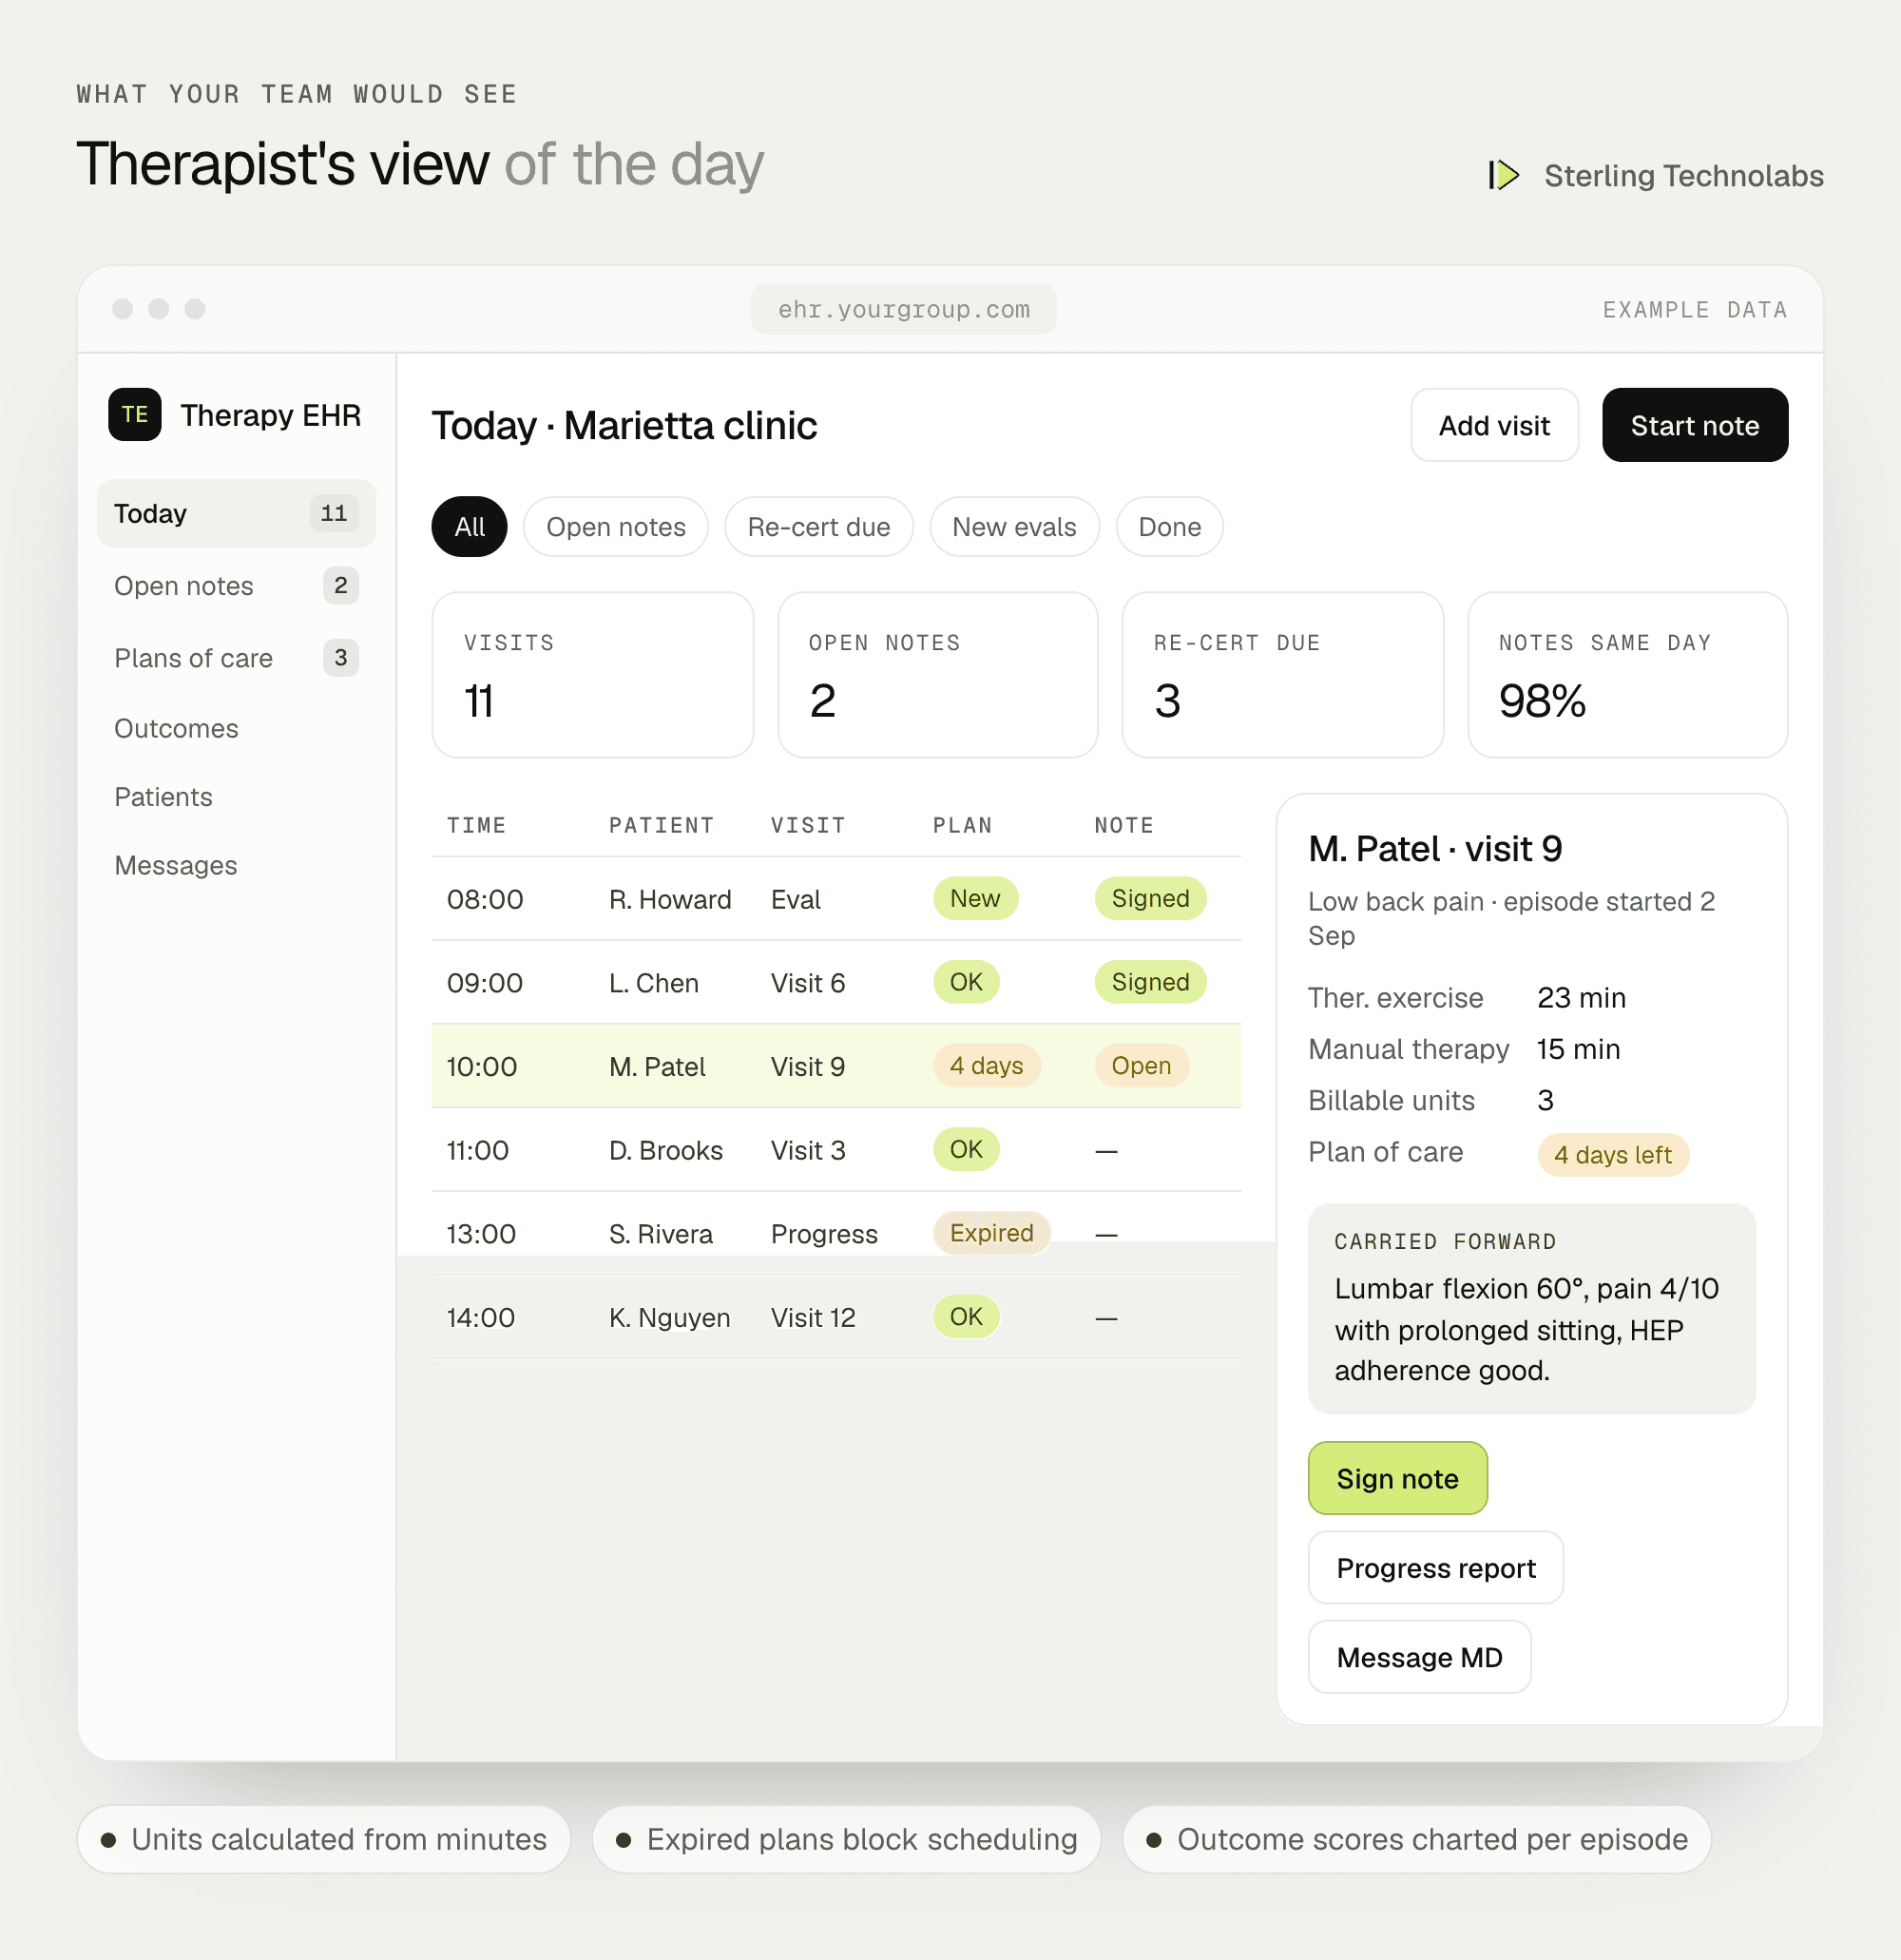
Therapists see today's schedule, notes still open, plans of care due for re-certification and outcome scores due. The note screen carries forward the last visit's findings so they only record what changed.
EHR features by user
| Therapists | Front desk and billing | Clinic and group leaders |
|---|---|---|
| Therapy note templates | Multi-clinic scheduling | Visits and cancellations by clinic |
| Plan of care and goals | Eligibility and authorizations | Outcome scores by diagnosis |
| Minutes and units per code | Claim checks before submission | Plans of care at risk |
| Home exercise programs | Patient reminders | Therapist productivity |
Data and integrations
| Integration | What it's for | Example options |
|---|---|---|
| Clearinghouse | Eligibility checks and claims | Clearinghouse API (837 and 835) |
| Billing | Payments, denials, statements | In-house billing team or billing service |
| Referrals | Incoming referrals and records | E-fax, Direct messaging |
| Record sharing | Exchange with physicians and apps | FHIR R4 APIs |
| Patient messaging | Reminders and outcome links | HIPAA-eligible SMS and email |
| Data migration | Active patients and history | Export from the current EHR |
Delivery plan
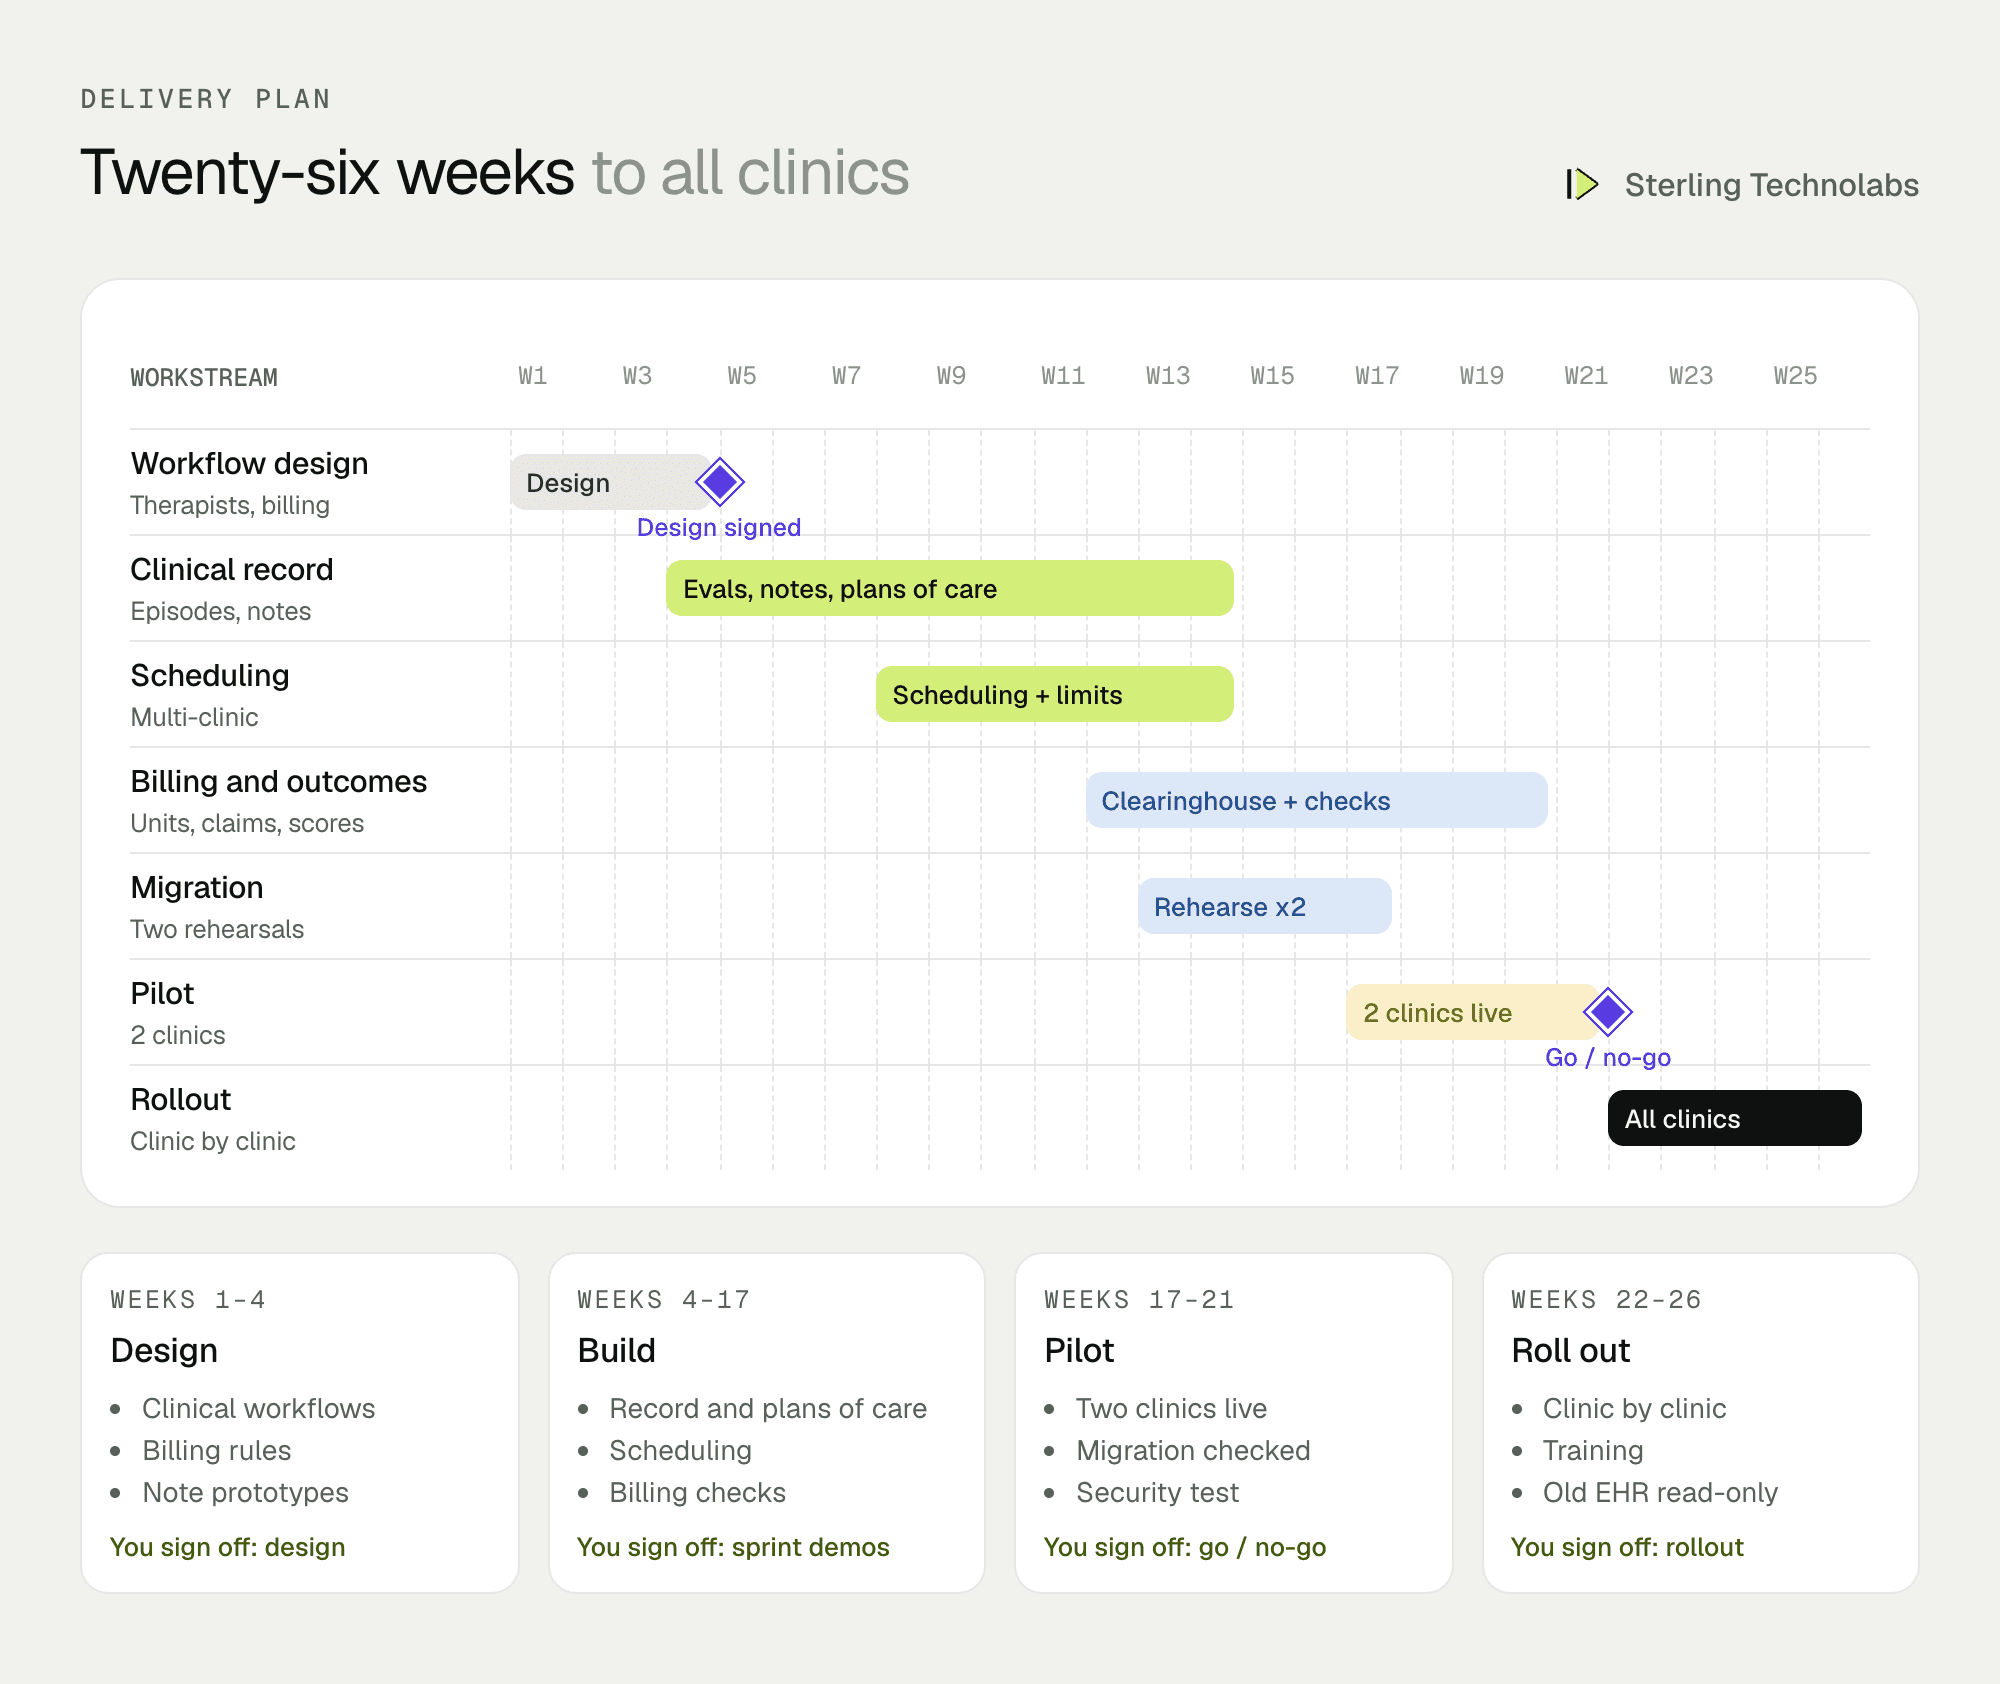
An EHR is not something to switch in one weekend. The first release covers documentation, plans of care, scheduling, billing checks and outcome measures. It runs in two pilot clinics while the old system stays available, then rolls out clinic by clinic. The patient app follows once every clinic is live. Data migration is rehearsed at least twice before go-live.
The team
| Role | Time | What they own |
|---|---|---|
| Solution architect | Part time | Data model, security, integrations, FHIR |
| Business analyst with healthcare experience | Full time | Clinical workflows, billing rules, UAT |
| Product designer | Weeks 1–10 | Note screens, scheduling, tests with therapists |
| Full-stack developers (3) | Full time | Clinical record, scheduling, billing checks |
| Flutter developer | After rollout | Patient app |
| QA engineer | From week 8 | Clinical scenarios, migration tests, security tests |
From your side: a clinical lead, a billing lead, two therapists from each pilot clinic, and your compliance officer.
What changes the effort
- Certification. Building to ONC certification criteria adds significant testing and documentation. Many specialty groups don't need it; some do.
- Billing scope. Claim checks with an outside billing service are simpler than building full revenue cycle management.
- Specialties. Adding occupational or speech therapy means more templates and rules.
- Migration. Active patients only is quicker than full history with documents.
- Patient app. Home exercise programs and reminders are a phase of their own.
Risks and how we'd handle them
| Risk | What we'd do |
|---|---|
| Clinicians reject the new notes | Therapists design and test the note screens, and pilot clinics run it before anyone else. |
| Data lost in migration | Two rehearsal migrations with record counts and spot checks signed off by clinic leads. |
| Billing errors | Billing rules tested against a year of past claims before they go live. |
| Security or privacy breach | BAA, role-based access, audit logs, encryption, penetration test before launch. |
| Scope keeps growing | A written first-release scope, and every new request goes into a later phase. |
What we'd measure
| Metric | How we'd measure it | Baseline from |
|---|---|---|
| Documentation time | Minutes from visit end to signed note | Current EHR audit log |
| Notes closed same day | Share of notes signed on the visit date | Current EHR reports |
| Lapsed plans of care | Visits scheduled after a plan expired | Spreadsheet tracking |
| Denial rate | Claims denied for documentation or units | Billing reports |
| Outcome completion | Episodes with start and discharge scores | Paper forms today |
Build or buy?
For most practices, buying a specialty EHR is the right decision. Custom EHR development makes sense for larger groups whose clinical model, billing rules or growth plans don't fit any product, who want to own their data and roadmap, or who plan to offer their platform to other practices. It is a multi-phase investment, and we'd rather tell you on the first call if a product will serve you better.
Questions we'd ask on the first call
- How many clinics, clinicians and visits a week?
- What EHR do you use today, and what are the biggest gaps?
- Do you need ONC certification for a quality program?
- Who handles billing, and what are your top denial reasons?
- What data would need to move from the current system?
FAQ
How long does EHR software development take?
A first release for a specialty group, with documentation, plans of care, scheduling and billing checks, typically takes six to seven months including a pilot and rollout. A patient app follows as a later phase.
How do you build an EHR system that's HIPAA compliant?
With the administrative, physical and technical safeguards HIPAA requires: BAAs with every vendor, encryption, access by role, audit logs, tested backups and security testing. Your own policies matter too, and we document our controls for your risk assessment.
Is custom EHR development better than buying one?
Only when your workflows, billing or plans don't fit available products. For most small practices, buying is better.
Can a custom EHR exchange data with other systems?
Yes. We expose records through FHIR APIs and connect to clearinghouses, referral channels and billing systems.
:: Typical stack
React, Node.js, PostgreSQL, FHIR R4 APIs, clearinghouse integration, Flutter patient app, HIPAA-eligible AWS
:: Related service
Custom software development
See the service

Send us your brief. We’ll help turn it into reality
A senior engineer replies within one business day with questions or a first plan: approach, team, timeline and estimate.
More blueprints like this


